How They Did IT: Measured, Benchmarked & Improved Oracle Health EHR Clinician Experience by 13%

How They Did IT: Measured, Benchmarked & Improved Oracle Health EHR Clinician Experience by 13%

Case Study: Rady Children’s Health Measured, Benchmarked & Improved Oracle Health EHR Clinician Experience by 13%

By Thomas Charlton, CEO Goliath Technologies

Objective measurement of the clinician’s lived digital experience when using Oracle EHR enabled evidence-based remediation, validated results, and a foundation for proactive experience management.

Executive Summary

Rady Children’s Health in Orange County faced a familiar healthcare technology problem: clinicians were reporting long login times, application slowness, and system instability, but the traditional technical metrics often suggested that the Oracle Health EHR environment was performing as expected. The missing element was an objective measure of what clinicians were experiencing at the point of care.

Goliath Technologies provided an Oracle EHR clinician experience measurement capability that established an empirical baseline across the clinician population and made previously invisible performance issues measurable. The baseline was evaluated against speed and reliability best-practice thresholds, allowing Rady Children’s to identify where experience was falling short, which clinicians and locations were affected, how frequently problems occurred, and where in the delivery chain the likely cause existed.

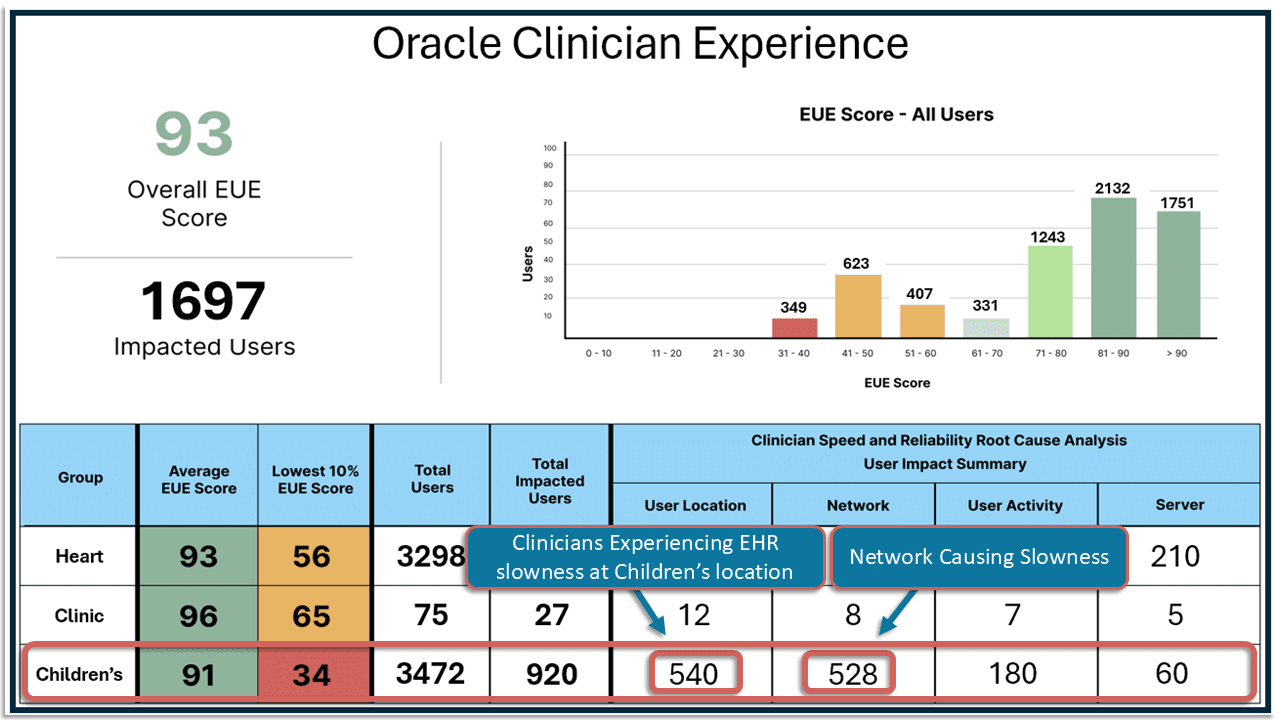
See the image below:
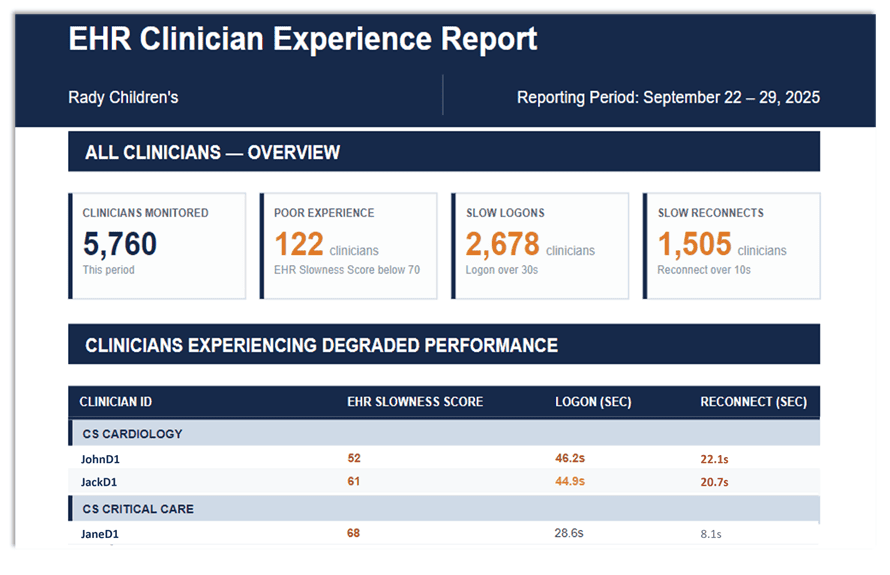
 

EHR Clinician Experience Report

The measurement became actionable. Clinical Informatics and IT used the evidence to prioritize targeted remediation—including replacement of laptops at specific locations, bandwidth increases, network switch upgrades, and identification of other focused IT resource improvements rather than making broad infrastructure investments based on assumptions. A subsequent measurement showed a 13% improvement in EHR speed and reliability from August to October 2025, validating the impact of the changes.

The engagement illustrates a repeatable model for clinician EHR experience improvement: measure the lived experience, benchmark it, act on the evidence, re-measure the outcome, and then use the same data proactively to manage performance over time.

“We practice evidence-based medicine on the clinical side. There is no reason we should not be practicing evidence-based decision-making in IT as well.”

– Dieter Sumerauer, MD, Associate CHIO, Rady Children’s Health


Background

Rady Children’s Health in Orange County, previously known as Children’s Hospital of Orange County (CHOC), uses Oracle Health Millennium to support clinicians and care delivery. Dr. Dieter Sumerauer, Associate Chief Health Information Officer, operates at the intersection of clinical care, informatics, and technology delivery — an increasingly important role as the digital experience of the EHR becomes inseparable from the clinical experience itself.

Clinicians had been raising concerns through email, Microsoft Teams, the help desk, rounding, and KLAS survey feedback. Those channels were important signals, but they could not answer the operational questions required to drive precise improvement: Who was affected? Where? How often? For how long? Was the issue in the Oracle-hosted environment, the local infrastructure, the endpoint, the network, or another part of the delivery chain?


Challenge: The Clinician “Lived Experience” Gap

The core problem was a disconnect between human feedback and technical reporting. Frontline clinicians experienced delays and instability, while infrastructure and application teams could look at conventional system metrics and conclude that the environment appeared healthy. Without empirical data describing the clinician’s actual digital experience, both perspectives could be true and neither side had enough evidence to resolve the disagreement.

New Clinician Experience Informatics

Traditional survey and rounding approaches are valuable for understanding sentiment, but they depend on voluntary participation, recall, and the time available for clinicians and informatics teams to provide or collect feedback. Rady Children’s needed a complementary approach: objective measurement of the experience being delivered to clinicians, at scale, and quickly enough to guide operational action.


Step 1: Measure the Clinician EHR Experience

Goliath was deployed to establish a baseline of the clinician digital experience while clinicians connected to and used Oracle Health Millennium. The Goliath difference is that they can deploy directly into the Oracle Hosted Environment (OHH or OCI) so that there is a true end-to-end picture of clinician experience from initial log on using Millennium. This approach connected human experience to empirical performance data, providing visibility into the technical delivery path from the clinician endpoint and Citrix/VDI environment through the Oracle-hosted infrastructure.

The measurement provided visibility into experience dimensions such as:

  • Login performance and long login events
  • Session and keystroke latency
  • Video and site slowness
  • Printing and dictation-related performance issues
  • Frequency and duration of poor experience
  • Affected clinicians, locations, devices, and infrastructure
  • Hosted versus client-side conditions contributing to the experience

Instead of waiting for a survey cycle or relying only on the clinicians who reported a problem, the organization could evaluate the experience across the clinician population and establish an objective baseline in a matter of days.


Step 2: Benchmark Performance Against Best-Practice Thresholds

Measurement alone is not enough. The data must be put into context. Goliath compared the observed speed and reliability experience against established performance thresholds and best-practice criteria to identify where clinician experience was performing well and where it required attention.
This benchmarking approach converted thousands of individual performance observations into a practical improvement framework. Clinical and IT leaders could focus on the clinicians, sites, workflows, and components that materially deviated from expected performance rather than treating every complaint—or every infrastructure component—as equally likely to be the problem.


Step 3: Turn the Benchmark into Actionable Data

Once the baseline and performance gaps were visible, the data was used to isolate likely causes and determine where remediation would have the greatest impact. The evidence also helped bring Oracle, internal IT, application teams, and Clinical Informatics into the same conversation with a common set of facts. The analysis led to targeted actions supported by the observed data:

  • Replacing laptops at specific locations where data showed slowdowns and devices had exceeded their replacement lifecycle
  • Increasing bandwidth to affected sites
  • Replacing network switches that were limiting throughput
  • Identifying under-resourced VDI infrastructure servers contributing to performance problems
  • Using end-to-end visibility to distinguish Oracle-hosted conditions from client-side infrastructure issues

Step 4: Re-Measure and Validate the Outcome

After remediation, Rady Children’s measured the clinician experience again. The follow-up assessment provided an objective before-and-after view of whether the changes improved the experience delivered to clinicians.


13% IMPROVEMENT

Oracle Health EHR Speed & Reliability
August 2025 → October 2025

The 13% improvement demonstrated the value of treating clinician EHR experience as a measurable operational outcome. Rather than if an infrastructure investment, configuration change, or remediation project had worked, the organization could verify the result using the same experience data that established the original baseline.

Step 5: From Benchmarking to Proactive Experience Management

The value of the measurement did not end with the assessment. Rady Children’s began thinking about how the same data could be used continuously by both IT and Clinical Informatics. For IT, clinician experience data creates an opportunity to identify performance trends and emerging issues before they become widespread complaints or clinical disruptions. For Clinical Informatics, it provides objective evidence to advocate for clinicians, target rounding and improvement efforts, and communicate transparently about whether the EHR experience is improving. Dr. Sumerauer also described plans to share performance metrics with clinicians through a monthly newsletter, helping clinicians see login-time trends and other indicators of system performance. This transparency can strengthen trust by showing that the organization is measuring and responding to the same issues clinicians experience every day.

A Repeatable Clinician Experience Improvement Model

The core problem was a disconnect between human feedback and technical reporting. Frontline clinicians experienced delays and instability, while infrastructure and application teams could look at conventional system metrics and conclude that the environment appeared healthy. Without empirical data describing the clinician’s actual digital experience, both perspectives could be true and neither side had enough evidence to resolve the disagreement.
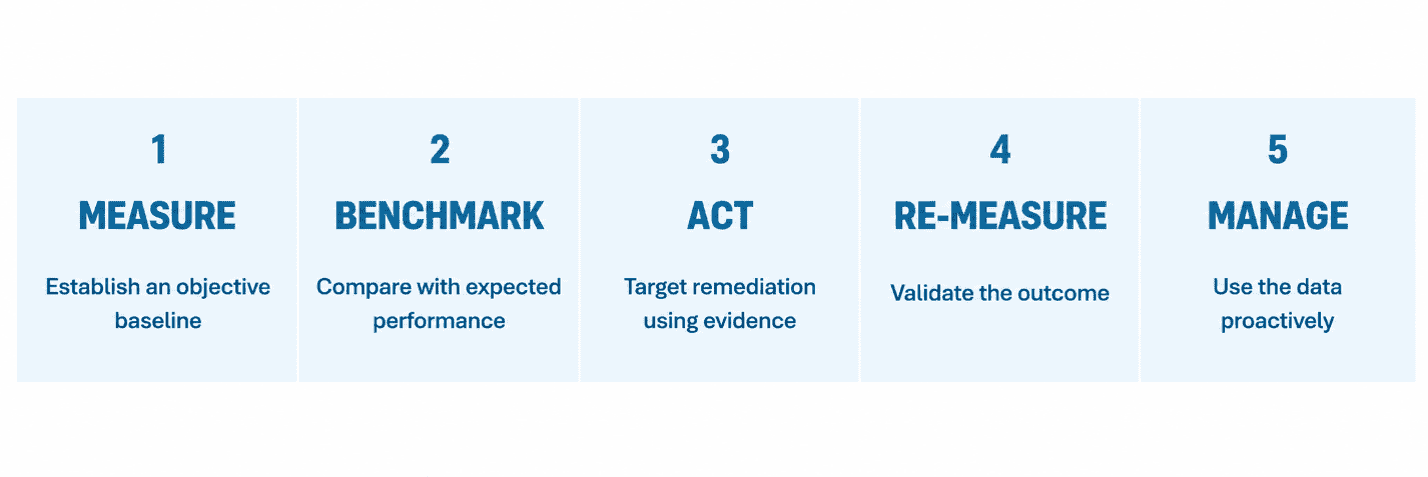
A Repeatable Clinician Experience Improvement Model

This cycle changes clinician experience improvement from a periodic perception exercise into a measurable discipline. The baseline establishes where the organization stands. Benchmarking identifies meaningful gaps. Actionable data directs resources toward the right problems. Re-measurement proves whether the intervention worked. Ongoing measurement then supports proactive management by IT and Clinical Informatics.


Key Outcomes

  • 13% improvement in Oracle Health EHR speed and reliability between August and October 2025
  • Objective visibility into the clinician’s lived digital experience
  • A baseline for evaluating experience across the clinician population
  • Benchmarking against speed and reliability best-practice thresholds
  • Identification of specific clinicians, locations, devices, and conditions associated with poor experience
  • Targeted, evidence-based remediation rather than broad speculative investment
  • A common set of facts for Clinical Informatics, IT, application teams, and Oracle
  • Before-and-after measurement to validate the impact of remediation
  • A foundation for proactive IT performance management and clinician advocacy

Key Insights

  1. Surveys tell you what clinicians perceive, measurement shows what they experience: Human feedback remains essential, but objective digital experience data can validate, quantify, and operationalize that feedback across the clinician population.
  2. Benchmarking creates context for action: A score is most useful when leaders can understand what is driving it and where performance differs from expected levels. Benchmarking helps separate normal variation from experience problems that deserve attention.
  3. Evidence improves investment decisions: When resources are finite, data can identify the specific endpoints, network components, sites, or systems that should be addressed rather than relying on broad upgrades and hoping the experience improves.
  4. Re-measurement closes the loop: Improvement initiatives should have a measurable outcome. Repeating the same clinician experience assessment provides evidence that the action taken produced the intended result.
  5. The same data can become an operating system for continuous improvement: Once measurement is established, IT can use it proactively to manage performance while Clinical Informatics can use it to advocate for clinicians, prioritize outreach, and create transparency around the experience being delivered.

Conclusion: Evidence-Based EHR Improvement

Rady Children’s experience demonstrates a different way to improve clinician EHR experience. Rather than beginning with a presumed technology problem or waiting for enough complaints to accumulate, the organization began by measuring what clinicians were experiencing. The measurement created a baseline. Benchmarking identified opportunities for improvement. The data guided targeted remediation. Re-measurement validated a 13% improvement. And the same visibility now provides a foundation for proactive management. For health systems seeking to improve clinician EHR experience, the lesson is straightforward: measure first, benchmark the experience, act on evidence, and measure again.


Learn More Here: EHR Speed & Reliability Improvement Program.

Source Notes

This case study was developed from Goliath Technologies’ interview with Dr. Dieter Sumerauer, Associate CHIO at Rady Children’s Health, and the July 2026 KLAS Summit presentation “How Informatics Improved EHR Speed and Reliability 13%.” The 13% result and August 2025 to October 2025 measurement period are drawn from the KLAS presentation. Quotations attributed to Dr. Sumerauer are drawn from the published Goliath interview.

About Goliath Technologies

Goliath helps ensure EHR speed & reliability for 25 million care interactions annually by providing at-the-elbow digital experience insights for 100% of clinicians without the need for self-reporting. Purpose-built for Epic, Oracle Health, and Meditech, Goliath provides the data that clinical and IT leaders use to understand EHR speed & reliability issues and implement fact-based initiatives to improve clinician experience.

How They Did IT: How Mt. San Rafael Used Data to Resolve vs Transfer Problems to Oracle

How They Did IT: How Mt. San Rafael Used Data to Resolve vs Transfer Problems to Oracle

How They Did IT: Mt. San Rafael | A New EHR Won’t Fix Old Problems


Go-Live Preparation:
Mt. San Rafael
A New EHR Won’t Fix Old Problems

By Michael Archuleta, CIO, Mt. San Rafael Hospital and Clinics


Let me say something that doesn’t get said enough before an EHR go-live: the problems your infrastructure has today will follow you into the new system.

Not pessimism. Just physics.

When you migrate to a hosted EHR environment like Oracle Health CommunityWorks, you are handing the keys to a new partner. Whatever was lurking in your on-premises environment gets inherited. A slow, unstable foundation doesn’t suddenly become fast and stable simply because a new application sits on top of it.

At Mt. San Rafael Hospital and Clinics, we signed with Oracle Health in December 2025. We chose Oracle Health CommunityWorks because it provides enterprise-grade infrastructure, modern capabilities, and an AI-native platform without the burden of maintaining a large internal IT organization. The decision was deliberate and strategic.

But signing a contract doesn’t guarantee a successful go-live.

Preparation does.

The goal was never simply to prepare for an Oracle Health go-live. The goal was to establish a foundation capable of supporting the next generation of healthcare technology.

Regardless of organization size, the challenge is the same: delivering reliable technology that enables clinicians to provide exceptional patient care. At Mt. San Rafael Hospital, we approach technology investments with the same discipline, accountability, and strategic rigor found in the nation’s leading health systems. Every decision must be supported by data, aligned with organizational objectives, and ultimately improve the clinician and patient experience.


Want to learn more? Request to speak with a healthcare IT consultant.

Challenge

The statistics surrounding EHR implementations are sobering. According to KLAS Research, only 38% of healthcare organizations report that their EHR transition fully met expectations. In the same research, 73% of organizations reported below-average clinician experience scores following implementation. KLAS data also demonstrates a strong relationship between system performance and clinician satisfaction. When physicians believe response times are adequate, satisfaction rises dramatically. When performance declines, satisfaction follows.

EHR speed and reliability are not simply technical metrics. They are foundational components of clinician experience.

As our Oracle Health implementation progressed, it became clear that we needed a more objective understanding of clinician experience within our environment.

Clinicians were reporting inconsistent logon times and occasional application responsiveness concerns. The feedback was legitimate, but the underlying causes were unclear. The challenge is that clinicians can tell you when something feels slow, but they cannot always tell you why. Identifying the “why” is what ultimately allows healthcare organizations to solve problems instead of simply reacting to symptoms.

The deeper concern was this: our Oracle Health go-live date was approaching, and any performance issue rooted in our on-premises virtual desktop infrastructure would not disappear when we flipped the switch.

In a CommunityWorks model, Oracle manages the hosted EHR environment. We own our infrastructure. If infrastructure issues exist within our environment, they remain our responsibility to address. Left unresolved, those issues become significantly more difficult and expensive to untangle after go-live.

We had one opportunity to get ahead of the problem.

I wasn’t going to waste it.


Solution

Oracle Health introduced us to Goliath Technologies as part of our go-live preparation process. Goliath’s platform is designed to provide healthcare organizations with visibility into what clinicians are actually experiencing when they interact with the EHR, without relying solely on self-reporting, help desk tickets, or manual observation.

We engaged Goliath to perform a Go-Live Infrastructure Health Check and Clinician Experience Measurement assessment.

Deployment was straightforward. Working alongside our local IT team, the platform was operational within days and began collecting performance data across our virtual desktop infrastructure environment.

The platform correlated session behavior, resource utilization, application performance, and user experience metrics across the environment. For the first time, we could objectively measure what every clinician was experiencing, regardless of location.

What stood out most was the ability to move from assumptions to objective measurements with minimal deployment effort. Instead of relying on anecdotal feedback, we now had visibility into the actual experience of every clinician utilizing the environment.

No surveys.

No waiting for complaints.

Just data.


What the Data Revealed

The findings came quickly, and they confirmed what I suspected: we had infrastructure issues that would have surfaced after our Oracle Health CommunityWorks go-live.

The analysis identified three distinct areas requiring attention.

  1. High Memory Utilization Across Sessions

More than 50% of clinician sessions were operating with elevated memory utilization. On the surface, user workflows appeared normal. However, underlying background processes were consuming resources that should have been available to clinical applications.

Without objective measurement, this issue would likely have remained invisible.

  1. VDI Disk Latency Impacting User Experience

The platform identified intermittent spikes in disk latency that directly correlated with degraded clinician experience.

These performance issues were subtle and episodic. Traditional monitoring methods would likely have missed them entirely. However, session-level analytics made the relationship between infrastructure performance and user experience unmistakable.

  1. CPU Ready Contention Across All Four Hosts

The most significant finding involved elevated CPU Ready metrics across all four virtualization hosts.

CPU Ready contention occurs when virtual machines are waiting for physical CPU resources. Those delays compound throughout the clinician experience, resulting in longer logons, slower application response times, and increased frustration.

Because the issue was distributed across the environment, no single user complaint would have identified the root cause.

The data did.

Taken together, these findings painted a clear picture: remediation needed to occur before go-live, not after.


Infrastructure Readiness is AI Readiness

One lesson became increasingly clear throughout this process: infrastructure readiness is no longer simply an EHR discussion.

It is an AI readiness discussion.

Healthcare organizations cannot expect to realize the full value of ambient documentation, predictive analytics, clinical decision support, intelligent automation, and future AI-enabled workflows if foundational infrastructure issues remain unresolved.

As healthcare continues its transformation toward AI-assisted care delivery, organizations that establish strong operational and technical foundations today will be best positioned to capitalize on tomorrow’s innovations.

Technology leaders who ignore infrastructure readiness may find themselves limiting the very innovations they hope to adopt.


Path Forward

Mt. San Rafael Hospital has engaged Goliath to support remediation efforts before our Oracle Health go-live.

The issues identified are fixable, and more importantly, they are fixable now, on our terms, with time to validate improvements before clinicians begin using the new platform.

The data has also allowed us to make targeted investments rather than broad assumptions. Instead of guessing where resources should be allocated, we now have objective evidence guiding our decisions.

Perhaps the greatest value of the engagement has been confidence.

Not perfect certainty, because healthcare technology rarely offers that.

But confidence that comes from understanding the environment, identifying root causes, and addressing issues before they impact patient care.


Lessons for CIOs Preparing for Go-Live

As we continue preparing for our Oracle Health implementation, several recommendations stand out:

  • Establish an infrastructure baseline before implementation.
  • Measure actual clinician experience, not just system uptime.
  • Validate concerns with objective data before making investments.
  • Address infrastructure bottlenecks before activation.
  • Treat infrastructure readiness as a patient care initiative, not simply an IT initiative.

The most successful go-lives are not defined by technology alone.

They are defined by preparation, execution, and the ability to remove obstacles before clinicians encounter them.


Final Thoughts

A mentor once told me that technology should never be the star of the show.

The patient should be.

As CIOs, our responsibility is not simply to implement technology. Our responsibility is to remove barriers that stand between clinicians and patients.

When infrastructure, workflows, applications, and people work together seamlessly, technology becomes nearly invisible. That is the true measure of a successful go-live.

Ultimately, success is not measured by activation dates or project milestones. It is measured by the ability of clinicians to focus on delivering exceptional care and by our ability as leaders to ensure that technology enables, rather than hinders, that mission.

That is how we build stronger healthcare organizations.

And that is how we ensure a patient’s ZIP code never determines their healthcare outcomes.

To learn more about how Goliath helps health systems surface and resolve clinician EHR experience issues, reach out directly at techinfo@goliathtechnologies.com or request to speak with a healthcare IT consultant.

If you would like to connect and share perspectives on EHR transformation, clinician experience, artificial intelligence, cybersecurity, or healthcare innovation, feel free to reach out: marchuleta@msrhc.org

About the Author

Michael Archuleta serves as Chief Information Officer at Mt. San Rafael Hospital and Clinics in Trinidad, Colorado. A nationally recognized healthcare technology executive and healthcare innovator, he is known for advancing cybersecurity, artificial intelligence, digital transformation, and technology-enabled care delivery. Under his leadership, Mt. San Rafael Hospital has earned HIMSS Stage 6 recognition, multiple Healthcare’s Most Wired awards, and national recognition for innovation in healthcare technology. Archuleta has been recognized by Becker’s Hospital Review as one of the nation’s top hospital and health system CIOs, is a HITEC 100 award recipient, serves on national healthcare advisory boards, and is a frequent speaker on leadership, cybersecurity, artificial intelligence, and digital transformation. He is a strong advocate for ensuring that a patient’s ZIP code never determines their healthcare outcomes.

Michael Archuleta

Michael Archuleta

Michael Archuleta is a highly respected leader in the field of Health Information Technology and serves as the Chief Information Officer of Mt. San Rafael Hospital in Trinidad, Colorado. He is widely recognized for his innovative and visionary leadership skills and has been honored with several awards and recognitions, including being named a Top Hospital and Health System CIO to know and receiving the HITEC 100 award, which recognizes the most influential Hispanics in the technology industry.

At-the-Elbow: Planning EHR Improvement Investments? Answer These Four Questions First

At-the-Elbow: Planning EHR Improvement Investments? Answer These Four Questions First

At-the-Elbow: Planning EHR Improvement Investments? Answer These Four Questions First

At-the-Elbow with Brian Patty, MD: Planning EHR Improvement Investments? Answer These Four Questions First

By Thomas Charlton, CEO Goliath Technologies


NEW digital experience data enables clinical and IT leaders to get the answers to critical questions before investing resources to improve EHR performance.

Healthcare organizations have spent years trying to improve clinician EHR experience through surveys, physician rounding, infrastructure investments, optimization projects, and training initiatives. While these efforts are often backed by strong business rationale, many organizations still lack objective data showing exactly which clinicians are struggling, why the experience is poor, and whether investments actually improved outcomes.

In this At-the-Elbow conversation, Dr. Brian Patty shares why the industry has historically operated in what he describes as a “whack-a-mole” model of clinician experience improvement, and how new technology is fundamentally changing that dynamic.

Want to learn more? Hear Dr. Patty live on June 18th – sign up here!

Thomas Charlton:

Dr. Patty, you’ve described improving clinician EHR experience as a game of “whack-a-mole.” What did you mean by that?

Dr. Brian Patty:

For years, health systems have depended on anecdotal complaints, physician rounding, and fragmented data to identify clinician experience issues. The loudest problems received attention first, but organizations rarely had visibility into the experience of all clinicians across the enterprise. That created a reactive cycle where teams were constantly chasing isolated complaints without understanding the broader patterns or root causes.

Thomas Charlton:

Why do you think health systems accepted this approach for so long?

Dr. Brian Patty:

Because, historically, there was no alternative. Organizations made decisions using the best information available at the time. Surveys and rounding were valuable because they created dialogue with clinicians, but they were inherently subjective, time-consuming, and impossible to scale across thousands of users in near real time. Clinical and IT leaders simply did not have access to objective clinician experience intelligence derived directly from the EHR ecosystem itself.

Thomas Charlton:

What has changed now?

Dr. Brian Patty:

What’s changed is that the data now exists. Through integrations with systems like Epic and Oracle Health, organizations can now measure clinician EHR experience directly from the technology clinicians use every day. That includes visibility into speed, reliability, workflow interruptions, and the infrastructure conditions contributing to degraded experience.

For the first time, health systems can move beyond assumptions and understand the digital experience of 100% of clinicians, not just the small percentage who respond to surveys or escalate issues.

Thomas Charlton:

How does that change decision-making for clinical and IT leadership?

Dr. Brian Patty:

It changes everything. Historically, organizations made large investments in infrastructure, optimization, training, or consulting initiatives without always having precise baseline data or a way to measure outcomes afterward.

Today, leaders can ask and answer four foundational questions before making those investments:

  1. What is the actual lived experience of my clinicians when they are using the EHR?
  2. If there are performance issues, how pervasive, frequent, and critical are they?
  3. What are the root causes of these performance issues so precision investments can be made to fix?
  4. Did my deployment of resources improve clinician experience?

That shifts organizations from reactive decision-making to precision improvement driven by evidence.

Thomas Charlton:

What does this mean for the future of clinician experience improvement?

Dr. Brian Patty:

I believe we are entering a new era where clinician experience improvement becomes measurable, operationalized, and proactive. Instead of reacting to isolated complaints, organizations can continuously monitor experience, identify emerging issues early, prioritize investments with confidence, and measure outcomes over time.

That is a fundamentally different operating model than the industry has had historically, and one that has the potential to significantly improve both clinician satisfaction and operational performance.

Hear Dr. Patty live on June 18th – sign up here.

To learn more about how Goliath helps health systems surface and resolve clinician EHR experience issues, reach out directly at techinfo@goliathtechnologies.com or request to speak with a healthcare IT consultant.

Brian Patty

Brian Patty, MD

Former CMIO Rush Medical Center

How They Did IT: Rady Children’s – Improved Oracle EHR Stability and Clinician Satisfaction by 13% with Evidence-Based Decision Making

How They Did IT: Rady Children’s – Improved Oracle EHR Stability and Clinician Satisfaction by 13% with Evidence-Based Decision Making

How They Did IT: Rady Children’s Improved Oracle EHR Stability and Clinician Satisfaction by 13% with Evidence-Based Decision Making

How They Did IT: Rady Children’s: Improved Oracle EHR Stability and Clinician Satisfaction by 13% with Evidence-Based Decision Making


By Thomas Charlton, CEO Goliath Technologies


In this How-They-Did-IT conversation, I sat down with Dr. Dieter Sumerauer, Associate Chief Health Information Officer at Rady Children’s Health in Orange County, to discuss how his team built the case for evidence-based IT decision-making, brought the right stakeholders together, and used data from Goliath to identify and fix the root causes of EHR performance problems their clinicians had been experiencing for years.

“What mattered was that none of our remediation actions were shots in the dark. We were not just upgrading infrastructure and hoping something improved. Each action was targeted and justified by the data. That is an important distinction, because IT budgets are finite and you cannot afford to make blanket investments hoping you hit the right issue.”

-Dieter Sumerauer


Want to learn more? Request to speak with a healthcare IT consultant.

Thomas Charlton:

Dr. Sumerauer, can you start by telling us a little about your background and your current role at Rady Children’s Health?


Dr. Dieter Sumerauer:

I’m the Associate Chief Health Information Officer at Rady Children’s Health in Orange County, which was previously known as CHOC, Children’s Hospital of Orange County. I joined about two years ago after serving as Medical Director of Ambulatory Healthcare Informatics for Pediatrics at University Hospitals of Cleveland. I started out in private practice, and early on I was doing things like wiring my own office and building wireless networks. That curiosity about the intersection of technology and care delivery has defined my career path ever since.


Thomas Charlton:

Let’s frame up what was happening at Rady’s before Goliath became part of the picture. What were you hearing from your clinicians, and what did your data actually tell you at the time?


Dr. Dieter Sumerauer:

The honest answer is that we didn’t know what we didn’t know. What we did know was that our frontline clinicians were complaining about long login times, overall system slowness, and the system not completing tasks, and ultimately crashing. And yet on the technical side, the prevailing view was that we were delivering good system stability and good speed to our end users.

There was a real disconnect. The people providing care on the front line were suffering, and the technical people were saying they couldn’t understand why, because everything looked fine on their end. The problem was that we had data on what we thought we were providing, but not on what was actually being delivered. It’s a bit like your internet service provider promising speeds up to 1 gigabit, while that may be the specification, it’s not necessarily what you’re getting at your device.

To borrow a phrase from Dr. Peter Pronovost at University Hospitals: “Waiting is suffering”. And I feel strongly that my real customer is the patient. Our clinicians are a conduit to that customer. When they are waiting for data, waiting for the system to respond, the patient is the one who suffers, waiting longer for answers, waiting longer for their physician to walk through the door. That is what was at stake.


Thomas Charlton:

How were you gathering feedback from clinicians before you had objective performance data? What channels were available to you, and where were the gaps?


Dr. Dieter Sumerauer:

We had multiple avenues via email, Microsoft Teams, the help desk, and a KLAS survey. We were working hard to collect as much input as we could. But you can only “round” so much, and there are only so many hours in the day. What you really need is the evidence to back up what your end users are telling you. Without that, you end up in a frustrating standoff: clinicians are saying something is wrong, and the technical team is pointing to infrastructure metrics that look healthy. Everyone is entrenched in what they think they know.


Thomas Charlton:

Your CHIO, Dr. Steve Martel had been advocating to bring Goliath in for two years before it finally happened. What was the tipping point? And when we eventually engaged together, you took a leadership role in pulling all the right parties into the room – Oracle, the internal IT team, the application team. Can you walk us through how that came together?


Dr. Dieter Sumerauer:

At the same time you and I connected, which happened when we met at the KLAS summit in Salt Lake City, I had already been in conversations with Oracle about why some of these performance issues were occurring. The responses we kept getting were, essentially, “it’s not on our end.” I was not convinced.

So, it became about relationship-building and getting the right people at the table. We were post-pandemic, and people were not coming on site. I pushed to get Oracle’s team to actually come in and experience what our frontline physicians were experiencing firsthand. And while we had them here, it made sense to also have Goliath present to test the connections and look at how the product was actually being delivered to end users.

The data turned out to be illuminating for everyone, our internal technical team and the Oracle team alike. We found problems on both sides, though more of the issues ultimately traced back to our environment. That was important. It moved the conversation from defensiveness to shared accountability.


Thomas Charlton:

Once the data was in hand, what specific actions came out of it? I’m thinking about the targeted investments that were made based on what Goliath surfaced.


Dr. Dieter Sumerauer:

The data was genuinely eye-opening. It showed us that we really did not know what we thought we did. We ended up replacing laptops at specific locations where the data showed slowdowns, devices that had exceeded their replacement lifecycle but had not been flagged through our normal processes. We increased bandwidth to affected sites. We replaced network switches that were limiting throughput. We also identified end-of-life servers in our server farm that were contributing to the problem.

What mattered was that none of these were shots in the dark. We were not just upgrading infrastructure and hoping something improved. Each action was targeted and justified by the data. That is an important distinction, because IT budgets are finite and you cannot afford to make blanket investments hoping you hit the right issue.


Thomas Charlton:

Going forward, you’ve mentioned using this data not just retrospectively but proactively. How are you thinking about the ongoing role of performance visibility at Rady’s?


Dr. Dieter Sumerauer:

The data is only valuable if you act on it, and ideally if you act on it before users start complaining. If we are actively monitoring trends, we should be able to use the data predictively, identifying when a system is trending toward a problem before it surfaces as a clinical disruption.

On the transparency side, I plan to publish performance metrics through our monthly clinician newsletter, essentially speed dials that tell our end users how the system is performing, whether login times are improving, and where we are relative to where we were. Transparency builds trust. When clinicians see that you are measuring and responding to the same things they care about, the relationship between IT and the clinical side changes.


Thomas Charlton:

You have a clear point of view on the evolving role of the CHIO. Can you share how you think that role is changing, particularly in relation to the technical side of delivery?


Dr. Dieter Sumerauer:

I think the separation between clinical informatics and the technical infrastructure world is artificial, and we are recognizing that more and more. You are seeing more clinicians move into CIO roles, and I believe that is because the field has finally acknowledged that you cannot have a good product if it is not delivered efficiently.

The CHIO used to be focused almost exclusively on the clinical tools within the EHR, like the order sets, the documentation templates, and decision support. And those things matter. But if the system crashes when a physician tries to access it, or if it takes 90 seconds to log in, none of that other work matters. The delivery mechanism is part of the product. To not give me visibility into the technical delivery side of things is to hamstring me in my ability to serve my end users and, ultimately, the patients.

That is why you are increasingly seeing CMIOs and CTOs working together more directly, and why the conversations at health system leadership level are starting to bridge those two worlds.


Thomas Charlton:

Final question: for CMIOs and CHIOs who find themselves in a situation similar to where you were with clinicians complaining and technical teams confident everything looks fine, what would you tell them?


Dr. Dieter Sumerauer:

Get the data. To best advocate for your clinicians, you need evidence to support the claims they are making. Without that evidence, it is very hard to move anything, because people get entrenched in what they think they know.


We practice evidence-based medicine on the clinical side. There is no reason we should not be practicing evidence-based decision-making in IT as well. Once you have that evidence, once you can show where the problem actually exists in the delivery chain, the case becomes clear-cut. Without it, you are guessing. And in healthcare, guessing costs people time, and time costs patients.


To learn more about how Goliath helps health systems surface and resolve clinician EHR experience issues, reach out to techinfo@goliathtechnologies.com or learn about the Goliath EHR Speed & Reliability Improvement Program.

Dr. Dieter Sumerauer

Dieter Sumerauer

MD, FAAP | Rady Children’s

Transformative physician leader with proven success in process improvement and innovation. Experienced in informatics and change management with a record of team building and collaboration.

How They Did IT: Days to Hours – Southwell & Oracle Health Transformed Issue Resolution

How They Did IT: Days to Hours – Southwell & Oracle Health Transformed Issue Resolution

How They Did IT:
Days to Hours – Southwell & Oracle Health Transformed Issue Resolution

How They Did IT: Days to Hours – Southwell & Oracle Health Transformed Issue Resolution


By Thomas Charlton, CEO Goliath Technologies


In this How-They-Did-IT conversation, I sat down with Jamey Pennington, CIO of Southwell Health, to discuss a recent frontline engagement where Goliath worked with the IT teams at Southwell Health and Oracle Health in a collaboration effort to resolve issues causing clinician frustration when using the Oracle EHR.


Thomas Charlton:

Jamey, what are your responsibilities as CIO of Southwell Health?

Jamey Pennington:

My division covers all things, technology, except for biomedical equipment. That includes the EHR, ERP systems, clinical informatics, telecommunications, and infrastructure. While biomed is technically separate, those lines blur in healthcare, so we work closely together. Ultimately, my responsibility is to make sure the technology environment supports clinicians and the organization.

Thomas Charlton:

What was your path into healthcare IT, and how technical do you believe today’s healthcare CIO needs to be?

Jamey Pennington:

I started in healthcare IT pulling wires through medical office buildings and connecting terminals to Unix systems. That technical foundation has been extremely valuable, especially when challenging vendors and evaluating overlapping tools. Today’s CIO must balance innovation while minimizing duplication and control costs by leveraging enterprise platforms.

Thomas Charlton:

Can you frame up the situation at Southwell when you first reached out to Goliath?

Jamey Pennington:

We were dealing with infrastructure changes and limited resources. Clinicians were experiencing freezing systems, session lockups, and forced logouts when using the Oracle EHR. This directly impacts clinical workflows and patient care. With multiple technologies involved, troubleshooting was extremely complex and there was quite a bit of trial and error or educated guessing about what might be causing the issues. We were working with our service provider, and of course, Oracle Support in an attempt to find the root cause of the issues, but we were unsuccessful.

Keep in mind, when these types of issues occur and the clinician is having slowness or application crashes in a patient care setting, it is very disruptive and causes acute frustration. I am very aware of the fact that EHR performance issues contribute to physician and nurse burnout, so it is something that receives immediate escalation and attention.

Thomas Charlton:

How long were these issues occurring before you contacted Goliath?

Jamey Pennington:

It is important to remember that when clinicians and users report issues there is very little actionable data. They describe what they are experiencing, for example, an application freezing up, but beyond that there is little data to go on to begin a troubleshooting sequence.

The issues went on for about a month and when we called Goliath, we were just shooting arrows in the air trying to hope something hits.

Thomas Charlton:

So how did you do IT or find a solution?  

Jamey Pennington:

As you know we called you all and first pulled together a meeting with Oracle Support, our internal team, and our service provider to bring you up to date. Then your team really began to examine the data both current and historic. This is critical because, as I said earlier, you don’t get actionable feedback from users and sometimes the incident being reported isn’t fully accurate in terms of date, time, and location. This is an enormous challenge and detailed data from Goliath was critical.

Specifically for this situation, I knew that Goliath is deployed in the Oracle Hosted Environment which provides extremely valuable clinician experience data. Your team ran reports immediately looking back 30 days and could see data on 100% of the clinicians in terms of who was having problems, frequency, duration, and root cause. Also, your product pulls in performance data from our on-premises infrastructure, so we have a complete end-to-end picture.

We are an Oracle First health system, and we were working together closely on this issue, and I think I speak for all of us that we didn’t as much care where the problem was, we just wanted it fixed, so a single view of both environments was critical.

I don’t want to get into the specifics around the exact root cause and where it existed, but I can tell you that without the added visibility and support that Goliath provided, we would likely still be chasing the problem today.

It was one of those issues where the description of the problem – application freezing and session lockups – was so broad that we literally had to check everywhere. After a month of fighting these issues with multiple partners and with many hours expended, Goliath was able determine the exact root cause in a single call over two hours and we applied a fix that resolved the issues permanently.

Thomas Charlton:

Oracle EHR being a hosted application wasn’t an issue when it came to troubleshooting?

Jamey Pennington:

As with any hosted application, we must rely on the team that is managing the hosted environment to contribute to the troubleshooting process. Oracle Health Support was fully engaged but they don’t see beyond their hosted environment. At Southwell, we operate in a double-hop Citrix environment which means the two environments are totally separate, which adds a layer of complexity when it comes to management and troubleshooting.

Goliath has a special partnership with Oracle and can see both environments from a single console. Having this independent and intelligently correlated performance data allowed us to see the clinician connection path fully from the initial connection at a remote location through to accessing Millennium. This enabled us to isolate the root cause and work collaboratively with Oracle using a common data set from Goliath, which included both environments.

Thomas Charlton:

Pivoting a bit from this issue but related, how do IT and clinical leadership collaborate at Southwell?

Jamey Pennington:

We work closely with our CMIO. Transparency and shared understanding are critical. Seeing problems firsthand helps convert subjective feedback into actionable improvements. In fact, I commonly do rounding with clinicians in person to proactively understand their perspective and identify issues you can’t see unless you are with them personally. It also builds confidence.

Thomas Charlton:

What are your keys to success as a healthcare CIO?

Jamey Pennington:

My core focus areas are balancing innovation with regulatory compliance; transparency is essential of course, as well as clear communication to build trust and alignment across teams.

Thomas Charlton:

How do you see healthcare IT evolving in the next 24-36 months?

Jamey Pennington:

AI will play a major role, particularly in diagnostics, transcription, and automation. Strong governance will be critical to maximizing benefits while minimizing risk.

Thomas Charlton:

Do you have a final takeaway for the readers?

Jamey Pennington:

Improving clinician experience and patient care requires collaboration, frontline engagement, and data-driven decisions. Aligning Clinical and IT teams around shared facts enables faster resolution and better outcomes.


If you would like to discuss further, reach out to techinfo@goliathtechnologies.com or learn about the Goliath EHR Speed & Reliability Improvement Program.

Jamey Pennington

Jamey Pennington

VP | Chief Information and HIPAA Security Officer, Southwell

Oracle Health EHR Is Slow? Data Reveals the True Bottleneck

Oracle Health EHR Is Slow? Data Reveals the True Bottleneck

Oracle Health EHR Is Slow? Data Reveals the True Bottleneck

When Oracle Health EHR Is Slow: What the Data Reveals About the True Bottleneck​

By Thomas Charlton, Goliath Technologies


When Oracle Health EHR is slow, clinicians often assume the bottleneck is the application vendor. In reality, the data often shows the root cause sits in the client-side ecosystem – network, virtualization, endpoints, or session performance – well before Oracle’s hosted environment.

“Goliath offers great observability by giving us objective measurement of clinician satisfaction with Millennium and the analytics to foster a productive, data-driven dialogue between our IT staff and Oracle to resolve issues.”

– Jamey Pennington, CIO, Southwell Health


The Perception: Oracle Health EHR is the Root Cause of Performance Issues

Oracle Heath EHR Children Hospital Network Slowness V2

NOT SO FAST!


The Reality: A Complex IT Ecosystem


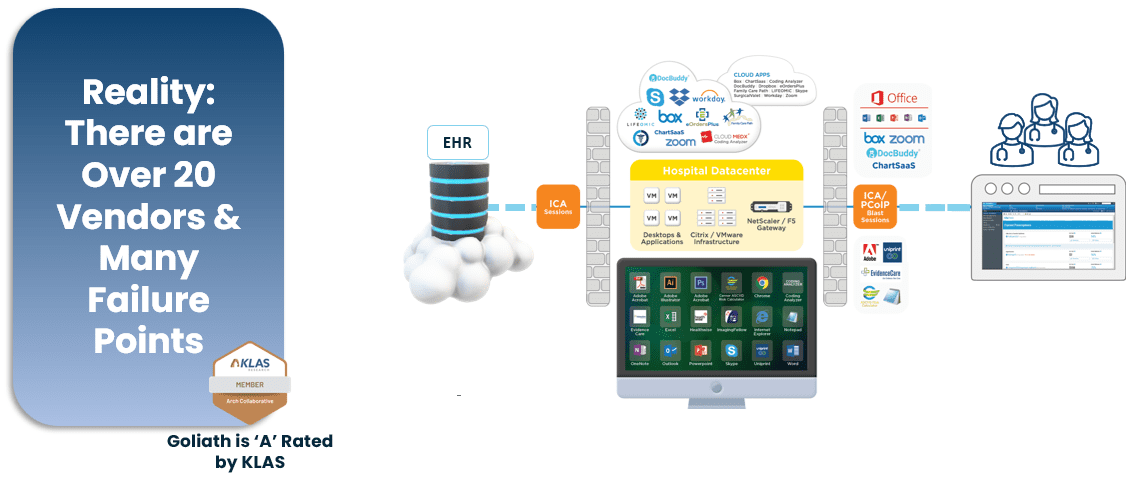
In truth, performance issues are rarely that straightforward. As illustrated below, there are multiple IT infrastructure elements, applications, and other variables between the clinician and the EHR application.


Oracle Heath EHR Reality
Over the last decade, we’ve participated in numerous Incident Response Calls (IRCs) and troubleshooting sessions with Oracle Health EHR clients. From these experiences, three key takeaways stand out:

1. Most speed & reliability issues attributed to Oracle Health EHR originate on the client side.

2. Clients lack the necessary data to identify and isolate these client-side issues.

3. With the right data, clients can resolve issues faster—without escalating to Oracle.

Why Oracle’s Hosting Isn’t Usually the Issue

Oracle Health EHR operates in a highly controlled, well-managed hosting environment with robust performance monitoring. It has been our experience, when attempting to resolve speed and reliability issues, that the client doesn’t have the same visibility into their IT infrastructure and end users as Oracle does, so there isn’t a common set of facts upon which to build a resolution plan. Oracle has very complete performance data, while the client has limited insight into the IT elements and many variables that can impact clinician experience. This incomplete picture on the client side results in many hours of wasted time attempting to isolate the root cause of issues.

Having the Right Data Matters

In an Oracle Health hosted environment, accurately isolating the root cause of clinician experience issues requires access to the right operational and experiential data — not assumptions or self-reported feedback. Because Oracle hosts and manages the core infrastructure, most traditional IT monitoring tools lack visibility into what clinicians actually experience at the point of care. Through Goliath’s exclusive access to Oracle-approved clinician experience and performance telemetry, healthcare organizations gain objective, real-time insight into session performance, application responsiveness, and end-user experience. This unique data foundation enables IT and clinical leadership to quickly differentiate between EHR application issues, network latency, virtualization performance, and endpoint constraints – dramatically reducing troubleshooting time and allowing teams to focus remediation efforts where they will have the greatest clinical impact.

Here is an example from an actual health system we worked with recently on a project to improve speed and reliability.


Oracle Heath EHR Perception
Troubleshooting any hosted application is complex, but without the right performance data, it becomes nearly impossible. This is where end-user experience analytics make a difference.

While we don’t claim that Goliath Technologies is the answer to every issue, we do provide a unique level of visibility that Oracle Health EHR clients simply don’t have elsewhere. With our technology, you can:

· See exactly which clinicians are experiencing performance issues.

· Identify issue frequency, duration, and likely root cause.

· Eliminate guesswork and reduce reliance on clinician self-reporting.

If you would like to discuss further, reach out to techinfo@goliathtechnologies.com or learn about the Goliath EHR Speed & Reliability Improvement Program.

Ryan Oliver

Thomas Charlton

Thomas is Founder and CEO of Goliath Technologies.